
K.MANASA, HALLTICKET NO:1601006081 - shortcase

"This is an online E log book to discuss our patient's de-identified health data shared after taking his/her/guardian's signed informed consent.  Here we discuss our individual patient's problems through series of inputs from available global online community of experts with an aim to solve those patient's clinical problems with collective current best evidence based inputs.  This E log book also reflects my patient-centered online learning portfolio and your valuable 

CASE OF MULTIPLE SKIN LESIONS 

A 23 year old lady , psychologist by occupation resident of nalgonda came to opd with c/c of painful skin leisions over the upper and lower limbs and back of trunk since 8 months 

HISTORY OF PRESENT ILLNESS:

Patient was apparently assymptomatic 8 months back she developed multiple red lesions on both upper limbs not associated with burning or itching after 1 week she developed itching and burning then she consulted local doctors who prescribed some medications but leisions didn't subsided so she referred to another hospital Where she diagnosed HENOCH SCHOLEIN PURPURA

EXAMINATION:

GENERAL PHYSICAL EXAMINATION:

patient is conscious, coherent,cooperative and moderately built and moderately nourished 

VITALS:

→ patient is afebrile

→ BP-110/80 mm Hg

→ PR-70 bpm

→ RR-16 Cpm

✓SpO2- 98%

✓GRBS - 122gm/dl

No Pallor, Icterus, Cyanosis, clubbing, Odema, lymphadenopathy.

ON INSPECTION:

red erythematous lesions Over Hands, legs, Palms and Soles including Web Spaces


CNS EXAMINATION:

  • Higher mental functions-normal 
  • Cranial nerves- intact
  • Sensory system- normal
  • Motor system- normal 
  • Meningeal signs- absent 
  • Cerebellar signs- absent

CVS EXAMINATION:

INSPECTION:

No scars sinuses and engorged ve

No visible pulsation

PALPATION:

apical impulse : heard in fifth inter coastal spac

ASCULTATION:

S1 and S2 heard

No murmurs 

RESPIRATORY SYSTEM EXAMINATION:


INSPECTION OF UPPER RESPIRATORY SYSTEM:

oral cavity- normal

Nose- normal 

Pharynx- normal 

LOWER RESPIRATORY TRACT:

INSPECTION:

trachea: central 

Symmetry of chest : symmetrical 

Movement: B/L symmetrical expansion of chest respiration

No scars, engorged veins or sinuses.

PALPATION:

All inspectory findings are confirmed by palpation.

Trachea: central - confirmed by three finger test.

Assessment of anterior and posterior chest expansion- B/L symmetrical expansion of chest.

No chest wall tenderness 

Vocal fremitus- normal

PERCUSSION:

done in sitting position 

Resonant

AUSCULTATION:

Vesicular breath sounds heard

Bilateral air entry present

No added sounds

ABDOMINAL EXAMINATION:

INSPECTION:

Shape : elliptical 

Quadrants of abdomen moving in accordance with respiration.

Umbilicus- central and inverted

No scars sinuses or engorged veins 

PALPATION:

No tenderness 

No organomegaly

PERCUSSION:

tympanic 

ASCULTATION:

Normal 

No organomegaly , no tenderness.

INVESTIGATION REPORTS:
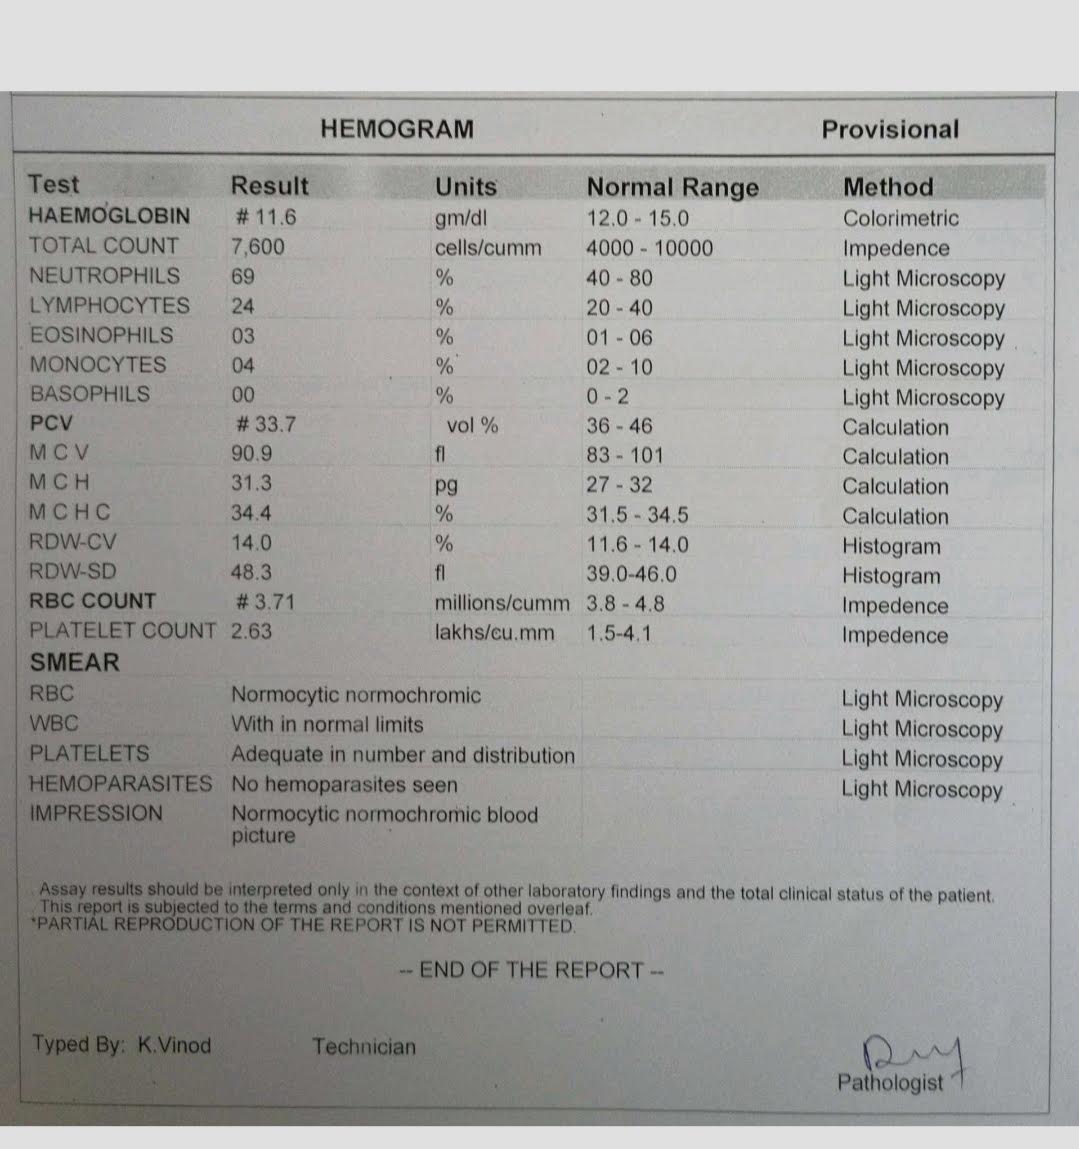


PROVISIONAL DIAGNOSIS: - HENOCH SCHONLEIN PURPURA ( Leucocytoclastic Vasculitis)

TREATMENT: 

At present patient is using:

Tab. Dapsone 100mgS

Syruporofer 5mlT

Tab Shelcal


Comments

Popular posts from this blog

A 19 YR OLD FEMALE

Unit 6 admission  A 19 yr old female, student by occupation & resident of Nagarjun sagar .came to casualty with  COMPLAINTS OF  1.Fever since 3 days 2.Vomitings 5 episodes since 1 day 3.Stomach pain since 1 day 4.Loose stools 2 episodes since 1 day 5. Cough with expectorantion since 1 day HISTORY OF PRESENT ILLNESS  : 1.FEVER - 3 days back she had -  Insidious onset of fever, low grade, intermittent type, Relieved on taking medications.subsided with in a day - Not associated with chills and Rigors. 2.VOMITINGS: - 5 episodes/ day since 1 day - non projectile,non bilious, contain food particles initially & later watery 3.STOMACH PAIN : - Diffuse type,increased after vomiting episode 4.LOOSE STOOLS : - 2 episodes/day - small inquantity - Not associated with pain abdomen, bloody stools -ve,Tenesmus -ve 5.COUGH WITH EXPECTORATION : - expectoration - small in quantity, light green color  - cough is not associated with diurnal variations,cough is more in r...

A 28 YR OLD MALE

UNIT 3 ADMISSION  A 28y old male came to the opd with chief complaints of fever since 10 to 25  days and SOB since 5 to 6 days. Patient was apparently asymptomatic 15 days back then developed fever which was incidious in onset and non progressive. It was associated with chills and dry cough. Not associated with cold. C/O SOB since 5 to 6 days that progressed from grade 2 to grade 3. Not associated with pedel edema and loose stools. No h/o bleeding manifestations, bleeding gums, malena, hemoptysis, hemetemesis. PAST HISTORY: No h/o similar complaints of in the past. No h/o DM, HTN, CAD, Asthma, TB. PERSONAL HISTORY : Patient has a mixed diet with decreased appetite and adequate sleep. Patient has constipation. Normal bladder filling and micturition. No addictions. No significant family history. GENERAL EXAMNATION: Patients is c/c/c. No pallor, icterus, cyanosis, clubbing, Vital2s lymphadenopathy, pedel edema. VITALS: temp: 101 F PR: 98 bump nd  RR: 18 cpm. BP: 90/70 mmhg. ...

A 45 YR OLD FEMALE

UNIT 6 ADMISSION  A 45 old female came to casualty with  COMPLAINTS OF  1.Fever since 4 days 2.Vomitings since 4 days 3.Loose stools since 4 days Patient was apparently asymptomatic 4 days back 1.FEVER Was low grade,intermittent not associated with chills & rigors 2.VOMITINGS  -5 to 6 episodes/day,non bilious non projectile,food/water as content  3.LOOSE STOOLS  -2 to 3/day,watery in consistency,no blood/mucous in stools associated with abdominal discomfort  - pt had h/o intermittent high colored urine(she described as red) -SOB intermittently since 1 month associated with orthopnea PAST HISTORY  Pt was apparently asymptomatic 3 yrs back,then pt had  - Pain in B/L knee - 3 yrs causing unable to walk properly for which she used to take NSAIDS for severe pain  - 2 MONTHS BACK: She slipped from staircase,had fracture of Rt tibia & underwent surgery 1 month back in a hospital in nalgonda & also got diagnosed to be diabetic .since...